Leukoencephalitis in Newborn due to Dengue Infection in Mother
1. Patient Presentation
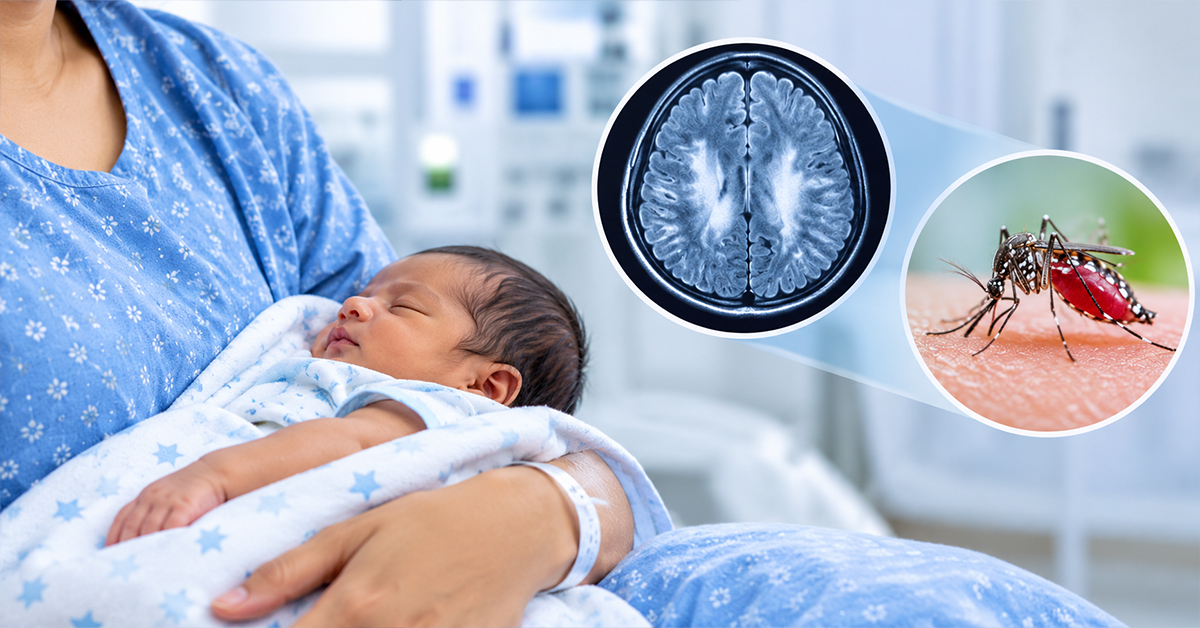
A term female newborn with a birth weight of 3 kg, appropriate for gestational age (AGA), was delivered on 20 October 2021 to a dengue-positive primigravida mother.
Following delivery, the baby was initially shifted to the mother’s side. However, the newborn developed respiratory distress, cyanosis and oxygen desaturation. The baby was referred to a local paediatrician, where intubation and mechanical ventilation were initiated.
As the baby’s general condition worsened and sclerema developed, the newborn was referred to MAEER’s Vishwaraj Hospital for further management in an intubated state with bag and tube ventilation.
2. NICU Admission and Initial Management
The newborn was admitted to the Neonatal Intensive Care Unit (NICU) and placed on SIMV-PSV mechanical ventilation.
The initial management included:
-
IV access was secured, and necessary investigations were performed.
-
The baby was kept nil by mouth (NBM) and started on intravenous fluids.
-
IV antibiotics, Inj. Meropenem and Inj. Vancomycin, were initiated due to suspected severe sepsis, and blood culture was sent.
-
Due to weak pulses, an IV normal saline (NS) bolus was administered, followed by inotropic support.
-
In view of deranged coagulation profile and low haemoglobin, Fresh Frozen Plasma (FFP) and Packed Cell Volume (PCV) transfusions were given on Day 3.
3. Management of Severe Sepsis and Respiratory Distress
Laboratory investigations indicated severe sepsis, elevated inflammatory markers and electrolyte disturbances. Intravenous Immunoglobulin (IVIG) was administered, and electrolyte imbalances were corrected accordingly.
Due to repeated episodes of oxygen desaturation on conventional mechanical ventilation, the baby was shifted to High-Frequency Oscillation (HFO) ventilation on Day 3.
The baby maintained oxygen saturation on HFO and was gradually shifted back to conventional mechanical ventilation on Day 5.
In view of recurrent seizure episodes:
-
Anticonvulsant treatment was initiated.
-
Inj. Midazolam infusion was started and continued for 48 hours.
-
The medication was subsequently tapered gradually.
4. Infection Management and Further Investigations
Considering severe sepsis and the deranged septic profile, Inj. Fluconazole was added due to suspected fungal sepsis.
Blood culture findings were suggestive of Serratia marcescens, which was sensitive to Inj. Meropenem and Inj. Vancomycin. Following the culture findings, Fluconazole was discontinued.
CSF examination was normal, and antibiotic treatment was continued for a total of 14 days.
As the sclerema gradually decreased, the baby developed generalised body oedema. Inj. Lasix and intravenous albumin infusion were administered for the management of oedema associated with hypoalbuminaemia.
5. MRI Brain Findings
MRI Brain revealed lacunar signal intensities involving:
-
Right gangliocapsular region.
-
Right occipital region.
-
Bilateral parafalcine regions.
-
Left parietal subcortical white matter.
Diffusion restriction was noted, suggestive of acute demyelinating encephalitis.
6. Further Respiratory and Infection Management
Repeated attempts were made to wean the baby from SIMV ventilation to CPAP. However, these attempts were unsuccessful due to inadequate spontaneous respiration.
A repeat septic screen was positive, and repeat blood culture was suggestive of Enterobacter cloacae.
The following management was undertaken:
-
Inj. Meropenem and Inj. Vancomycin were restarted.
-
Laboratory investigations showed elevated inflammatory and infection parameters.
-
Antibiotics were upgraded to Piptaz and Gentamycin and continued for seven days.
7. Recovery and Clinical Progress
Gradually, the baby’s general condition and laboratory parameters started improving.
-
Nasogastric tube (NGT) feeding was initiated and gradually increased according to tolerance.
-
Persistent hypokalaemia was investigated to rule out Bartter syndrome.
-
Urinary investigations showed raised urinary calcium and an increased urinary calcium/creatinine ratio, with normal serum magnesium.
-
The baby was gradually shifted to Non-Invasive Positive Pressure Ventilation (NIPPV) and subsequently to T-piece ventilation.
8. Successful Weaning and Discharge
The baby was successfully weaned from ventilatory support and placed on oxygen through nasal prongs at 1 litre/minute.
The newborn was accepting breastfeeding and expressed breast milk (EBM) orally every two hours.
The baby was vitally and haemodynamically stable and was discharged with follow-up advice.
9. Final Discharge Diagnosis
The final discharge diagnoses included:
-
Term female newborn, birth weight 3 kg, appropriate for gestational age.
-
Born to a dengue-positive primigravida mother.
-
Early-onset sepsis.
-
Leukoencephalitis.
-
Culture-positive neonatal sepsis.
-
Respiratory distress.
-
Disseminated Intravascular Coagulation (DIC).
-
Neonatal seizures.
-
Electrolyte imbalance.
-
Neonatal hyperbilirubinaemia.
10. Treating Consultant
Dr. Chandrakant Sahare
MBBS, DCH, DNB
HOD – Pediatrics
11. Paediatric and Neonatology Team
Dr. Mahesh Shinde
Sr. Consultant – Pediatrics & Neonatology
Dr. Rohan Chaugule
Jr. Consultant – Pediatrics & Neonatology
Dr. Nilesh Upre
Jr. Consultant – Pediatrics & Neonatology
Dr. Mahendra Surawase
Jr. Consultant – Pediatrics & Neonatology
Dr. Swati Ghasle
Jr. Consultant – Pediatrics & Neonatology
12. Comprehensive Mother & Child Care at MAEER’s Vishwaraj Hospital
One step further in caring for you and your newborn.
-
Natural Childbirth Oriented Care
-
Labour & Delivery Rooms with Comfort of Home
-
Level 3 NICU
-
High-Risk Pregnancy Care
-
Dedicated Team of Obstetricians, Pediatricians and Anaesthetists
-
Lactation Consultants, Dietitians and Physiotherapists
24×7 Emergency Services: 020 6760 6060
Website: www.vishwarajhospital.com
More Case Study